Hub · Peptide Science
What are peptides? Meaning, medicines, safety and legal status in Australia
Peptides are short chains of amino acids, the building blocks of proteins. Many occur naturally in the body. There they help with signalling for growth, metabolism and tissue repair (TGA peptide products page, updated 23 September 2026). Some peptides are approved medicines, such as insulin. Many peptide products promoted online in Australia are unapproved. The Therapeutic Goods Administration (TGA) has not checked their safety, quality or effectiveness.
Form Labs materials are research reference materials, not the approved medicines; no Form Labs product is approved for human or veterinary use.
01MeaningContents
- 01Meaning
- 02Types
- 03Steroids
- 04Medicines
- 05Why medicine records differ
- 06Top peptides
- 07Read records, not rankings
- 08Adverse events
- 09Label warnings
- 10Research
- 11Public interest
- 12C-peptide
- 13C-peptide levels
- 14Foods
- 15Collagen peptides
- 16Legitimacy
- 17What a research label means
- 18Import and sale
- Comparison
- FAQ
- Sources
One short word, a dozen different things. Search for peptides and the results mix many items. There is a hormone from your own pancreas and a diabetes medicine. There is a collagen powder, a skin serum and a vial sold on social media. They share a name because they share a structure. They do not share a purpose or a safety record.
This page is part of the peptide science hub. It answers the questions people ask most about peptides, one at a time. The answers come from regulator pages and published studies. Each answer names the source, the study model and the limits. It gives no directions for use. Research material is not a medicine.
Key facts
| Definition | A chain of amino acids joined by peptide bonds (TGA, 23 September 2026) |
|---|---|
| Length used by peptide databases | Fewer than 50 amino acids (Hamdani et al., Protein Science, 2026) |
| Typical therapeutic peptide mass | 500–5,000 daltons (Wang et al., 2022) |
| Approved peptide drugs worldwide | More than 80 (Wang et al., 2022; Muttenthaler et al., 2021) |
| Peptides in clinical development | More than 170 (Wang et al., 2022) |
| Peptide drug sales in 2019 | More than $70 billion worldwide (Wang et al., 2022) |
| Regulation in Australia | Depends on contents, promotion and intended purpose (TGA, 23 September 2026) |
| Regulator pages checked | 14 October 2026 |
What are peptides?
A peptide is a short chain of amino acids, the small units that make up proteins (TGA peptide products page, 23 September 2026). Peptide bonds join neighbouring amino acids. Databases of peptide structures count a chain as a peptide when it has fewer than 50 amino acids. So the word peptide describes a structure, not a purpose. Insulin, a collagen supplement, a cosmetic serum and an unapproved product sold online can all be called peptides. Each has a different legal status in Australia.
Your body makes peptides all the time. Pancreatic beta cells release insulin, a peptide hormone, into the blood. The TGA says natural peptides help with the signalling that governs growth, metabolism and tissue repair. Peptides made as medicines usually weigh 500 to 5,000 daltons. That sits between small-molecule drugs and large proteins. How peptides are built, bond by bond, has its own page.
For readers in Australia the question has a legal edge. The TGA says a peptide product is regulated as a therapeutic good if it is promoted, supplied or generally used for a therapeutic purpose. Products with claims for cosmetic purposes only may be regulated as cosmetics instead. The Australian law hub sets out the schedule status of named compounds. This page covers the general questions.
What are the main types of peptides?
The sources checked for this page sort peptides in several ways. They do not use one list of four types. Three ways appear: by length, by origin and by job. By length, the MeSH vocabulary of the National Library of Medicine calls chains of fewer than 13 amino acids oligopeptides (MeSH record for Peptides). By origin, peptides come from the ribosome. They can also come from enzymes in bacteria and fungi. Or they can come from chemical synthesis. By job, they include hormones, host-defence peptides and cell-penetrating peptides.
Hormone peptides are the best known. Insulin, oxytocin, vasopressin and GnRH are natural hormones. GnRH is short for gonadotropin-releasing hormone. Their study started the field of therapeutic peptides. Host-defence peptides are also called antimicrobial peptides. Many living things make them. They can kill microbes directly. They can also shape the immune response.
Non-ribosomal peptides, such as vancomycin and cyclosporin, come mainly from bacteria and fungi. The sorting schemes overlap. A single molecule can be short, made by a cell and a hormone all at once. Cell-penetrating peptides are a group defined by one property. The FAQ below covers them.
Are peptides steroids?
No. Peptides and steroids are different chemical families. A peptide is a chain of amino acids. A steroid hormone is built from cholesterol. Cells turn cholesterol into steroid hormones in a series of enzyme steps. Testosterone has the formula C19H28O2 and no amino-acid chain (PubChem record for testosterone). The confusion comes from sport and regulation. Both families sit on the same lists. The World Anti-Doping Agency (WADA) 2026 Prohibited List puts anabolic agents, including steroids, in class S1. It puts peptide hormones, growth factors and mimetics in class S2. It bans both at all times (WADA 2026 list).
So a steroid peptide is not a standard category. People who search for it often mean a peptide that acts on the body's own steroid production. WADA lists such peptides in class S2.2.1. It calls them testosterone-stimulating peptides in males. They are chorionic gonadotrophin, luteinizing hormone, GnRH and kisspeptin (WADA 2026 Prohibited List, in force from 1 January 2026).
The phrase the new steroids is a comparison made in talk and media. The sources checked do not use it as a class. The TGA does say something in its 20 July 2026 media release. Peptide products continue to be promoted online for weight loss, anti-ageing, muscle growth, performance enhancement and cosmetic purposes.
Are peptides drugs, and which medicines are peptides?
Some peptides are medicines and many are not. The TGA lists insulin as an approved peptide-based medicine. So are insulin analogues. So are GLP-1 receptor agonists such as semaglutide. GLP-1 is short for glucagon-like peptide-1. So are oxytocin, desmopressin and octreotide (TGA guidance). More than 80 peptide drugs have been approved worldwide. Natural peptides in the body, peptides in food and cosmetic peptides are not medicines by default. Regulation depends on what is in each product. It also depends on how it is promoted and what it is for.
The table below lists selected peptide drugs approved since 2000. The uses come from their approvals. They are taken from Table 1 of Wang et al. (2022). Type 2 diabetes is the largest group in that table. Six GLP-1 receptor agonists were approved for it between 2005 and 2017. The range is wide. Osteoporosis, cancer, bowel conditions, pain and rare diseases all appear. The uses are the approved uses set by regulators. They are quoted for information.
By sales, the top-selling non-insulin peptide drugs in 2019 were three GLP-1 medicines. Dulaglutide (Trulicity) made $4.39 billion. Liraglutide (Victoza) made $3.29 billion. Semaglutide (Rybelsus) made $1.68 billion in retail sales. Worldwide peptide drug sales were above $70 billion. Those are 2019 figures, and this page reports no newer ones. The guide to the SURPASS and SURMOUNT trials shows how the trial record behind two of these medicines is read.
Why are some peptides medicines while others remain unapproved?
Doctors do use peptide drugs that have been approved. Each named drug has its own record. Sharing a name for a drug class does not mean sharing proof. The FDA flags safety concerns for CJC-1295 and ipamorelin. That risk list is not a drug approval.
The FDA safety page notes gaps in human data for CJC-1295. It also lists gaps in what we know about ipamorelin risks. Neither entry answers every question about harm.
The TGA practitioner page explains another point. Some access to unapproved drugs can occur under set rules. The TGA has not assessed those products for safety, quality or whether they work. The doctor must judge the risks and how well it was made. So unapproved does not mean no doctor ever handles it.
Is there a top, number one or most popular peptide?
No regulator or journal source checked for this page on 14 October 2026 gave a single ranking of peptides as a group. The question has no single answer. Rankings that can be checked use a stated measure. By 2019 retail sales, the top three non-insulin peptide drugs were GLP-1 medicines. By approvals, the field counts more than 80 peptide drugs and no single winner. By trial results, comparisons hold only inside one trial. One example is the 72-week SURMOUNT-5 trial. It compared tirzepatide with semaglutide in 751 adults. The maker of tirzepatide funded this open-label trial. It applies to those two medicines only.
Terms such as king and number one are marketing words. A fair ranking needs a stated goal, a stated measure and a head-to-head comparison. The head-to-head trials in the sources checked for this page concern approved medicines. None of the sources checked ranks the unapproved peptides promoted online. The TGA states that it has seen no scientific evidence for their safety or for the claims made for them (TGA advisory, 13 April 2026).
Some questions ask which three peptides a person should pick. That asks for a personal choice, and no source on this page can make one. The pages in the peptide science hub report what studies of single compounds found. They give the model, the size and the limits.
Why can no single peptide lead every ranking?
A ranking hides the question each study tried to answer. An approved drug has a record for a set use. A human study asks a question in one group. A cell or animal paper asks a narrower question. Those records cannot form one fair league table for every reader.
The TGA regulation page describes drugs with and without approval. A record for one medicine does not cover all peptides. That record does not cover every use someone might claim.
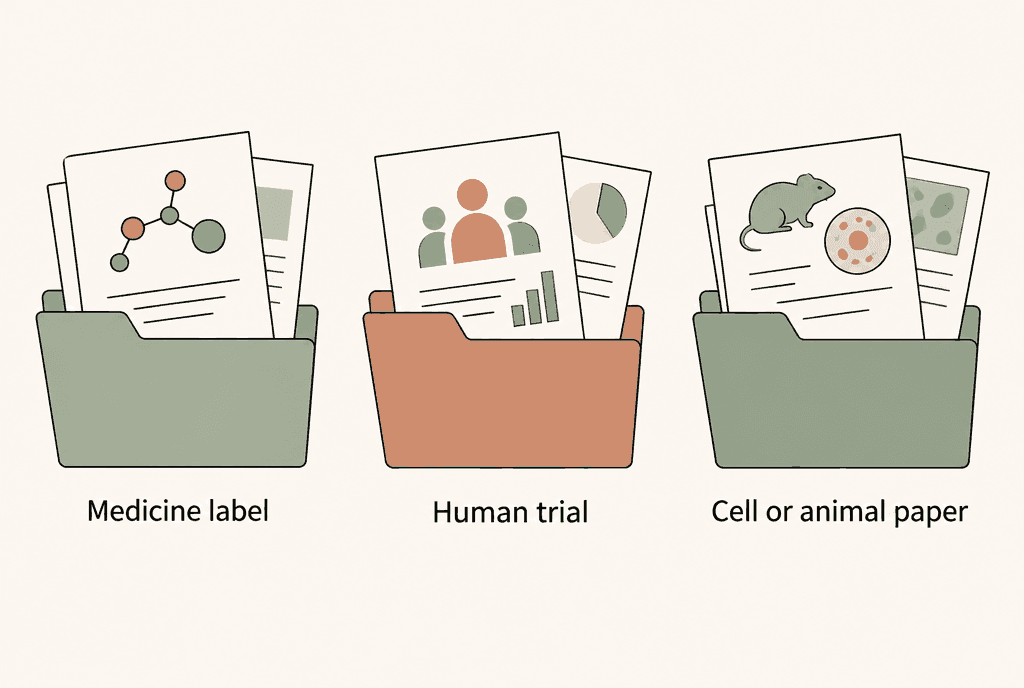
Picture three folders: medicine label, human trial, and cell or animal paper. Each folder holds a different kind of proof. The human-trial folder stays empty when a lab study looks promising. The approval guide keeps medicine records separate from research claims.
Evidence limits
What problems have been recorded with unapproved peptide products?
The TGA states that it has not assessed unapproved peptide products for safety, quality or effectiveness (TGA advisory, 13 April 2026). It lists what stays unknown about them. How are they made? Are they sterile? How do they work in the body? What side effects can they cause? What do they contain? Reports to the TGA for these products are single cases, not a measured rate. Some people had severe allergic reactions and needed adrenaline and hospital care. Some had severe body-wide inflammation and needed hospital care. Others had insomnia, blurred vision, extreme tiredness, joint pain and tendon injuries such as Achilles tendinitis.
A case the TGA published on 14 September 2026 shows why contents matter. A consumer said they used a product sold as retatrutide. They had uncontrollable vomiting and a torn oesophagus. They needed hospital treatment. The TGA tested one sample of the product, held in its original unmarked vial. It found undeclared semaglutide and no retatrutide. The semaglutide level was about 8 times the level in semaglutide products on the Australian Register of Therapeutic Goods. One report does not give a rate. The finding describes that sample (TGA advisory, 14 September 2026).
The TGA's page on buying peptide products online lists risks. Unapproved products may fall short of quality or safety standards. They may contain the wrong active ingredient. They may contain far more or less than the label states. They may not be sterile. They may cause serious adverse events, including severe allergic reactions, infection and liver damage (TGA, risks of buying online). A systematic review looked at BPC-157. It found 36 studies, of which 35 were preclinical and one was clinical. It reported that it located no clinical safety data within its search.
Which people do medicine labels exclude, and what do they say about liver and kidneys?
Prescribing information for approved peptide medicines says who should not take them. It also gives warnings. These come from trials. Take the US label for Ozempic (semaglutide, a GLP-1 medicine; revised June 2026). It lists two contraindications. One is a personal or family history of medullary thyroid cancer. The same goes for multiple endocrine neoplasia syndrome type 2. The other is a serious allergic reaction to semaglutide (DailyMed Ozempic label). The label also warns of acute pancreatitis. It warns of gallbladder disease. It warns of acute kidney injury from fluid loss.
Those lists belong to one medicine. They do not carry over to other peptides. An unapproved product has no label of this kind. The TGA says that a health practitioner may access an unapproved peptide product for a patient. Then the practitioner is responsible for judging its quality and safety, because the TGA has not assessed it (TGA practitioner page).
The label for another approved peptide, bremelanotide (Vyleesi), lists a different contraindication. It is uncontrolled high blood pressure or known heart disease (DailyMed Vyleesi label). The difference shows that each label reflects its own trials. No single list of exclusions covers all peptides.
On liver and kidneys, the TGA lists liver damage as one serious harm that unapproved peptide products may cause. A 2025 systematic review covered 36 BPC-157 studies. It found no clinical safety data. The sources checked found no controlled human study of liver or kidney effects of the research peptides promoted online.
Is there much science behind peptides, and are peptides worth it?
Peptide science is large for approved medicines and thin for most products sold as research compounds. Insulin entered medicine almost a century ago. Since then, more than 80 peptide drugs have reached the market. They treat diabetes, cancer, osteoporosis, multiple sclerosis, HIV infection and chronic pain. More than 170 peptides are in active clinical development. BPC-157 is a peptide often discussed online. A 2025 systematic review found 36 studies of it. Of these, 35 were preclinical and one was a clinical report.
Worth it is a value judgement. Studies measure results in defined groups, not worth. Regulators ask a narrower question. Do the data on quality, safety and effectiveness support approval for a named use? The TGA states that approved peptide-based medicines are tested widely in human trials before approval (TGA guidance). Unapproved products have not had that check.
Evidence ranges from cell studies to large trials. The 72-week SURMOUNT-1 trial had 2,539 adults without diabetes. Mean weight change at week 72 was 15.0%, 19.5% and 20.9% across the three tirzepatide groups. It was 3.1% with placebo. This trial was of an approved medicine, funded by its developer. It says nothing about research material.
Why are so many people talking about peptides, and what about celebrity claims?
The TGA reports a big rise in the online promotion, advertising and supply of peptide products. It says they are promoted for weight loss, muscle growth, anti-ageing, recovery and performance enhancement (TGA media release, 20 July 2026; TGA peptide products page, 23 September 2026). No regulator or journal source checked measures how many people use peptides. So this page gives no figure. Claims about named public figures are interview or social-media statements. They are not clinical records. This page reports none of them.
Attention and evidence are different things. The TGA says unapproved peptide products are being advertised as delivering fast health results. They can pose serious health risks (TGA media release, 20 July 2026). The TGA also says that influencers and online sellers who promote unapproved peptide products may be held accountable for unlawful advertising. A name attached to a product is a promotion, not a study.
Questions about what a particular celebrity or podcaster takes have no sourced answer either. No peer-reviewed paper or regulator page found for this page records what any named person takes. So the record in the sources checked is empty.
What is C-peptide, and why is it measured instead of insulin?
C-peptide is a 31-amino-acid peptide cut from proinsulin, the precursor molecule. Pancreatic beta cells release it in equal amounts with insulin. Labs measure C-peptide instead of insulin because it stays in the blood longer. C-peptide has a half-life of 20 to 30 minutes. Insulin has 3 to 5 minutes. The liver removes about half of the insulin secreted but almost none of the C-peptide. This gives a steadier reading of the body's own insulin output. C-peptide is also called the proinsulin connecting peptide.
Insulin made by the body and insulin made as a medicine look alike to an insulin test. But C-peptide tells them apart. C-peptide does not come from insulin made as a medicine. So a C-peptide result reflects the person's own pancreas, even in someone treated with insulin. The biological role of C-peptide itself remains poorly understood.
The role of C-peptide in insulin production is mostly one of origin. Cleavage of proinsulin yields insulin and C-peptide in equal amounts. That equal split is why a C-peptide measurement works as a proxy for insulin secretion.
What is a good C-peptide level, and what do high or low levels mean?
No single good C-peptide level exists. Labs use different assays and units, and ranges depend on the population tested (Jones and Hattersley, Diabetic Medicine, 2013). In healthy people, fasting plasma C-peptide is reported as 0.3 to 0.6 nmol/L. It rises to 1 to 3 nmol/L after a meal. A level below 0.2 nmol/L is linked with a diagnosis of type 1 diabetes in that review. Clinicians read results in context, not alone. A high level means the pancreas is releasing a lot of insulin. This can occur with insulin resistance. The meaning of a given level depends on the person.
Reading a C-peptide result is a clinical task. Blood C-peptide can read falsely high in kidney impairment, because the kidneys remove about half of C-peptide. The meaning of a given level depends on a person's insulin resistance. A person with obesity and insulin resistance may have normal or high C-peptide even with autoimmune type 1 diabetes. So high values do not point to one cause. C-peptide testing also helps assess insulinoma. This is a tumour that secretes insulin.
The sources use three units. 1 nmol/L equals 1,000 pmol/L and 3 ng/mL. A value is meaningless without its unit and the lab's own range.
Which foods contain peptides?
Every food that contains protein contains amino acids linked by peptide bonds. Digestion breaks food proteins into peptides and amino acids. Food proteins also carry hidden peptide sequences that can act as signals once released. Reviews call them food-derived bioactive peptides. No ranking of foods by total peptide content was found in the sources checked. The one direct food measurement found covers glutathione, a tripeptide. A 1992 survey found it moderate to high in fruits and vegetables. It was relatively high in freshly prepared meats. It was low in dairy products, cereals and breads. This measures one compound. It does not rank foods by total peptide content.
Absorption decides which peptides reach the blood. The intestine takes up di- and tripeptides through a transporter called PEPT1. That transporter does not accept free amino acids. It does not accept peptides of four or more amino acids. The gut breaks longer peptides down first. The food-peptide reviews add that well-designed clinical trials of food-derived peptides remain scarce.
A 1992 survey measured glutathione in foods. Processing and preservation other than freezing generally reduced the measured glutathione. This finding concerns that tripeptide. It does not measure total food-peptide content.
What has been recorded about the safety of collagen peptides?
The sources checked for this page record one allergy finding for fish-derived collagen. They also record a call for more long-term safety research. They give no measured rate of adverse events. A 2000 study looked at 10 children with fish allergy. Three had IgE antibodies to fish gelatin, which is type I collagen. IgE antibodies are the immune proteins behind allergic reactions. So fish collagen might be an allergen in people with fish allergy. The small study did not test collagen supplements. A 2025 narrative review of hydrolysed marine collagen says future research should focus on long-term safety.
The 2021 meta-analysis of 19 randomised, double-blind, controlled trials had 1,125 participants. It focused on skin outcomes, not safety. So it cannot settle safety questions. The 2025 marine collagen review is a narrative review. It sums up other studies and ran no trial of its own.
A 2000 lab analysis tested serum samples from three small patient groups (10, 2 and 15 patients). IgE antibodies showed little cross-reactivity between fish and bovine gelatins. The study did not test hydrolysed collagen supplements. The peptide comparison guide sets marine and bovine collagen side by side.
Are research peptides legitimate, and how can anyone check a peptide seller?
Legitimate has two separate meanings: lawful and verifiable. On lawfulness, the TGA states that a research use only or not for human use disclaimer does not change whether a product is regulated as a therapeutic good (TGA, how peptides are regulated). On verifiability, you cannot judge a seller from its own website alone. The TGA warns that unapproved products may be wrongly labelled. They may hold far more or less active ingredient than the label states (TGA, risks of buying online). Records bear on both meanings. The supplier checklist lists ten of them.
A certificate of analysis (COA) is a test report for a named batch. It documents only the lot, the compound and the test method it names. A report for a different lot says nothing about another batch.
This page does not rank or review named sellers. Reviews, most trusted lists and company comparisons rest on opinion. None of the regulator or journal sources checked evaluates individual suppliers. The TGA says it works with the Australian Border Force to stop unlawful imports of unapproved peptide products.
Does a research-use line settle whether a website sells a drug?
No. A research-use line alone does not settle that question. In a March 2026 warning letter, the FDA examined claims across a website. It found human-use claims despite the research label. The use shown by those claims mattered. That US finding does not decide the status of every Australian product.
The FDA letter dated 31 March 2026 records that specific finding. It is not a blanket ruling about every research material. Names on a label and claims about the body can point in different directions.
The FDA sample guidance covers samples studied in a lab. Samples used only for basic research fall outside the drug rule described there. That narrow rule does not clear peptide sales websites. The records concern different things with different uses.
Can peptides be brought into Australia, seized at the border or sold here?
Can you import or sell a peptide product in Australia? It depends on its status on the Australian Register of Therapeutic Goods (ARTG). You cannot import or supply an unapproved peptide product unless an exemption, approval or authority applies. The Personal Importation Scheme covers an import only if every condition is met. One is use by you or your close family. Another, for prescription-only medicines, is a valid Australian prescription (TGA guidance; TGA scheme page). Goods that fail the conditions may be seized and destroyed. The buyer can lose the goods and the money.
The TGA's 7 May 2026 advisory says the peptide imports it sees are often poorly labelled. It does not release vials it cannot identify under the scheme. It will tell the Australian Border Force to seize them (TGA advisory, 7 May 2026). The scheme's 8 September 2026 changes make clear what proof travellers need. This applies to people coming to Australia with prescription-only medicines. The sources checked cover import into Australia. They do not address airline rules for domestic flights.
Selling is a separate question. The TGA says it is generally unlawful to advertise unapproved therapeutic goods to the Australian public. It says supply of unapproved goods is banned unless an exemption applies. Civil penalties under the Act go up to $1.82 million per breach for individuals. For corporations they go up to $18.2 million per breach. Criminal penalties go up to 7 years in prison (TGA safety advisory, 14 September 2026). Anyone can report suspected unlawful supply or advertising to the TGA. The TGA has a form for this. The law hub covers schedule status by compound.
Comparison
Selected peptide drugs approved since 2000, as listed in Table 1 of Wang et al., Signal Transduction and Targeted Therapy, 2022. The list is partial and ends in 2020. It is a review's table, not a current Australian or US register. Approved uses are the regulators' approved uses as listed there. They are not advice.
| Medicine | First approval | Approved use as listed |
|---|---|---|
| Exenatide | 2005 | Type 2 diabetes |
| Liraglutide | 2009 | Type 2 diabetes |
| Semaglutide | 2017 | Type 2 diabetes |
| Pramlintide | 2005 | Type 1 and type 2 diabetes |
| Teriparatide | 2002 | Osteoporosis |
| Degarelix | 2008 | Advanced prostate cancer |
| Linaclotide | 2012 | Irritable bowel syndrome with constipation and chronic idiopathic constipation |
| Ziconotide | 2004 | Management of severe chronic pain |
| Tesamorelin | 2010 | Reduction of HIV lipodystrophy |
| Bremelanotide | 2019 | Hypoactive sexual desire disorder |
| Setmelanotide | 2020 | Chronic weight management of obesity |
FAQ
What are cell-penetrating peptides?
Cell-penetrating peptides cross cell membranes. They can carry other molecules into cells. Milletti sorted them by physical-chemical properties and origin (Drug Discovery Today, 2012). Guidotti and colleagues reviewed early tests of these peptides in disease models. Some tests led to clinical trials.
Why don't doctors use peptides?
Doctors do prescribe peptides. Insulin, GLP-1 medicines, oxytocin, desmopressin and octreotide are approved peptide-based medicines. Many are prescription-only (TGA guidance). For unapproved peptide products, the TGA says prescribers may apply for access through set pathways. Human studies should back the application. The studies should cover the specific peptide and its form. They should cover how it is given and what it is for (TGA practitioner page).
Which peptide acts like Viagra?
No peptide is a copy of Viagra. Viagra's active ingredient is sildenafil. It is a PDE5 inhibitor (DailyMed Viagra label). Wang et al. list two approved peptides in this area. Aviptadil was first approved in 2000 for erectile dysfunction. Bremelanotide was approved in 2019 for hypoactive sexual desire disorder. The Vyleesi label calls bremelanotide a melanocortin receptor agonist. It says the drug is not for men. It also says the drug is not to enhance sexual performance (DailyMed Vyleesi label).
Can peptides reduce wrinkles, and is there a peptide that acts like Botox?
A 12-week, split-face, double-blind trial covered 93 women aged 35 to 55. A palmitoyl pentapeptide moisturiser gave a significant improvement in wrinkles and fine lines against a control moisturiser. It was a single trial. It does not show results for other peptides. The sources checked for this page found no human trial comparing a peptide with botulinum toxin. The peptide comparison guide covers the limits.
What have studies found about peptides and injury repair or lower back pain?
For injury repair the evidence is mainly from animals. A 2025 systematic review of BPC-157 found 36 studies, 35 of them preclinical. It also found one small retrospective clinical report on chronic knee pain of unspecified cause. In it, 7 of 12 patients reported improvement lasting more than six months. That design cannot show cause. The animal findings do not show the same effects in humans. The review reported that it located no clinical safety data within its search. It reports no study of lower back pain.
Can peptides build muscle, and are they banned in sport?
The sources checked for this page include no controlled human trial of peptides promoted for muscle gain. The TGA says nobody has checked unapproved peptide products promoted for muscle growth. Their safety, quality and effectiveness are unchecked. The WADA 2026 list bans several groups at all times. These are growth hormone fragments and growth hormone-releasing peptides. They are also secretagogues. They are thymosin-beta-4 derivatives such as TB-500. It names BPC-157 among non-approved substances in class S0.
What peptide kills parasites?
The table of peptide drugs approved since 2000 in Wang et al. (2022) lists none for parasitic disease. Research is at the screening stage. A 2023 systematic review found 25 marine-derived cyclic peptides that act against parasites. Half of them (51%) were antimalarial. The rest were antileishmanial (27%) or antitrypanosomal (20%). It reports screening results and no human trial. Host-defence peptides made by living organisms can also kill microbes directly.
What peptides do celebrities and podcasters take?
No regulator page or peer-reviewed paper checked for this page documents what any named public figure takes. So no answer is given. Interview and social-media statements are not clinical records.
Is peptide therapy available in Perth?
Peptide medicines on the ARTG are prescribed by registered practitioners in Australia. Insulin and GLP-1 medicines are two examples. The TGA says many are prescription-only. A prescriber can seek access to an unapproved peptide only through set pathways. The Perth peptides hub covers delivery, documents and Western Australian law.
Can C-peptide be raised or lowered?
C-peptide measures the pancreas's own insulin output. So it changes when insulin secretion or kidney clearance changes. The sources checked describe it as a test result read alongside diabetes type, treatment and kidney function. They describe no method of changing it. A clinician interprets any result in context.
More in this hub
- Is SLU-PP-332 a peptide, and what harm record exists?
- What is SS-31, and did its trial measure weight loss?
- Which peptides are approved in Australia and by the FDA?
- What is a peptide bond? Peptide structure, chemistry and synthetic peptides explained
- Citrullinated peptide antibodies: what anti-CCP is, why the test peptide is cyclic and how it is pronounced
- Peptide vs protein: what is the difference? Peptides compared with proteins, hormones, collagen and approved medicines
- What do peptides do? What published studies found
- Peptide side effects: what studies and regulators have recorded
- Do peptides show up on drug tests? How peptides are tested and labelled
- What have collagen peptide studies measured about muscle?
- What is a signal peptide, and how does it direct a protein?
- What is carnosine, and what do studies measure?
- What is CGRP, and how does its signalling work?
- What is icotrokinra, and what do receptor studies measure?
- What is irisin, and how is it studied?
- What is lunasin, and what have studies measured?
- What is pramlintide, and how does amylin signalling work?
- What is peptide YY, and what do studies measure?
- What does TAT-DATNT refer to in peptide research?
Citations
22 sourcesWang L et al. Signal Transduction and Targeted Therapy. 2022;7:48.
doi:10.1038/s41392-022-00904-4Muttenthaler M et al. Nature Reviews Drug Discovery. 2021;20:309-325.
doi:10.1038/s41573-020-00135-8Hamdani R et al. Protein Science. 2026;35(10):e70779.
doi:10.1002/pro.70779Miller WL, Auchus RJ. Endocrine Reviews. 2011;32:81-151.
doi:10.1210/er.2010-0013Leighton E et al. Diabetes Therapy. 2017;8:475-487.
doi:10.1007/s13300-017-0265-4Jones AG, Hattersley AT. Diabetic Medicine. 2013;30:803-817.
doi:10.1111/dme.12159Shao R et al. International Journal of Molecular Sciences. 2026;27(1):483.
doi:10.3390/ijms27010483Mookherjee N et al. Nature Reviews Drug Discovery. 2020;19:311-332.
doi:10.1038/s41573-019-0058-8Milletti F. Drug Discovery Today. 2012;17:850-860.
doi:10.1016/j.drudis.2012.03.002Guidotti G et al. Trends in Pharmacological Sciences. 2017;38:406-424.
doi:10.1016/j.tips.2017.01.003Vasireddi N et al. HSS Journal. 2025;21:485-495.
doi:10.1177/15563316251355551Aronne LJ et al. New England Journal of Medicine. 2025;393:26-36.
doi:10.1056/NEJMoa2416394Jastreboff AM et al. New England Journal of Medicine. 2022;387:205-216.
doi:10.1056/NEJMoa2206038Chakrabarti S et al. Nutrients. 2018;10:1738.
doi:10.3390/nu10111738Daliri EB et al. Foods. 2017;6:32.
doi:10.3390/foods6050032Jones DP et al. Nutrition and Cancer. 1992;17:57-75.
doi:10.1080/01635589209514173Daniel H. Annual Review of Physiology. 2004;66:361-384.
doi:10.1146/annurev.physiol.66.032102.144149Bartoletti E et al. Clinical, Cosmetic and Investigational Dermatology. 2025;18:3339-3356.
doi:10.2147/CCID.S562518Sakaguchi M et al. Journal of Allergy and Clinical Immunology. 2000;106:579-584.
doi:10.1067/mai.2000.108499de Miranda RB et al. International Journal of Dermatology. 2021;60:1449-1461.
doi:10.1111/ijd.15518Robinson LR et al. International Journal of Cosmetic Science. 2005;27:155-160.
doi:10.1111/j.1467-2494.2005.00261.xRibeiro R et al. Marine Drugs. 2023;21:609.
doi:10.3390/md21120609
Continue
Research peptide reference material catalogueResearch use only, not for human or animal use.
Read the peptide science hubForm Laboratories supplies research-use-only reference material. This article is an educational summary of published third-party literature. It is not medical advice, not a use instruction, and research material is not for human or animal use.